

Trigeminal neuralgia (tic douloureux)
Trigeminal neuralgia is one of the most severe pains known to medicine. It arrives as sudden shocks through one half of the face, lasts seconds and stops as…

Prescription request online
A doctor will review your case and issue a prescription if medically appropriate.

Talk to a doctor online
Discuss your symptoms and possible next steps with a doctor online.


On this page
Medicines commonly prescribed for Trigeminal neuralgia (tic douloureux)
For informational purposes only. Always consult a doctor before using any medicine.
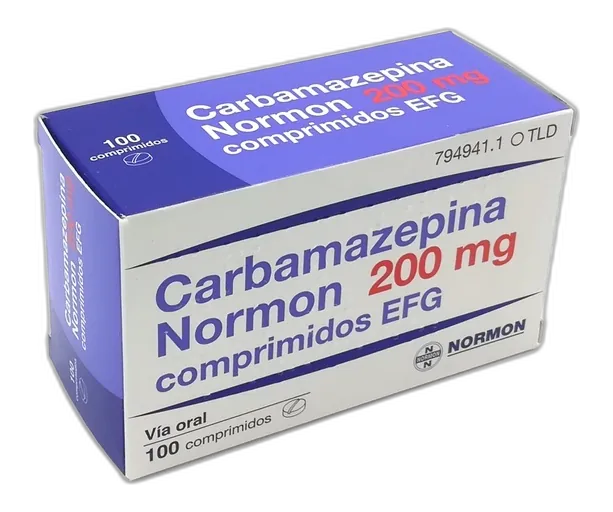 CARBAMAZEPINE NORMON 200 mg TABLETSIllustrative imageDosage form: TABLET, 200 mg carbamazepineActive substance: carbamazepineManufacturer: Laboratorios Normon S.A.Prescription required
 CARBAMAZEPINE NORMON 400 mg TABLETSIllustrative imageDosage form: TABLET, 400 mg carbamazepineActive substance: carbamazepineManufacturer: Laboratorios Normon S.A.Prescription required
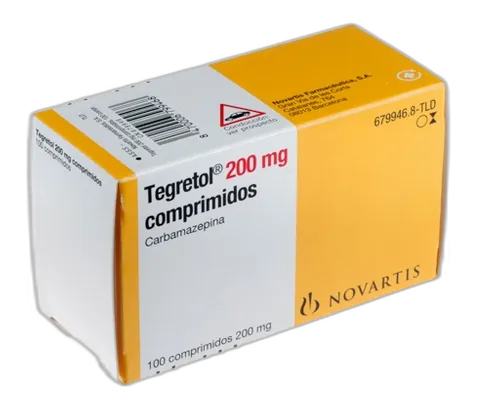 TEGRETOL 200 mg TABLETSIllustrative imageDosage form: TABLET, 200 mg carbamazepineActive substance: carbamazepineManufacturer: Novartis Farmaceutica S.A.Prescription required
Trigeminal neuralgia is one of the most severe pains known to medicine. It arrives as sudden shocks through one half of the face, lasts seconds and stops as abruptly as it began, and it can be set off by the brush of a towel, a mouthful of cold water or a gust of wind. Between attacks a person may feel perfectly well, which is exactly why the people around them so often fail to grasp the scale of it. Grasping it matters: this condition can be treated, but not with the things ordinarily used for pain.
What an attack is like
People describe the pain in almost identical terms: an electric shock, a stab, a flash, a jolt. It is sharp, one-sided and very short, from a fraction of a second to a couple of minutes. It is usually felt in the cheek, the upper or lower jaw, the teeth and gums, and less often in the eye and forehead. During an attack a person freezes and cannot speak or eat; from the outside it can look like a grimace or a twitch of the face, which is where the old name tic douloureux comes from.
Attacks come in runs: several a day, and in severe cases dozens or hundreds in twenty-four hours, week after week. The pain may then vanish for months or years, which is called remission. Over time these quiet periods tend to grow shorter.
The second recognisable feature is the trigger. Entirely ordinary actions set an attack off: chewing, swallowing, talking, smiling, brushing your teeth, washing your face, shaving or putting on make-up, a kiss, a cool draught, a car journey along a bumpy road. People start avoiding all of it — they stop brushing the teeth on the affected side, eat only soft food, refuse to go out on a windy day.
Why people spend years having their teeth treated
The pain is felt in the jaw and the teeth, so the first professional a person sees is nearly always a dentist. That is natural and not in itself a mistake: a diseased tooth, a crack or an infected root genuinely do need ruling out first.
What comes next, though, deserves to be said plainly: in trigeminal neuralgia people spend years having healthy teeth treated and pulled out. The reasoning is easy to follow — the tooth hurts, so the tooth must be the problem. One tooth is root-treated, the pain stays; the neighbouring one is root-treated, then extracted, then another. Sometimes several years and several teeth go by before anybody says the word "neuralgia".
The sign that should break the chain is pain that does not match what is found in the mouth. If the radiograph is clean, the tooth is sound, the treatment achieved nothing, and the shocks keep coming and are triggered by touch, what is needed next is not a dentist but a doctor — a family doctor or a neurologist. It is worth saying so out loud yourself: "my teeth have been checked and no cause was found; the pain is like a shock and touch sets it off." That sentence saves years.
Why the nerve becomes compressed
The trigeminal nerve is the main sensory nerve of the face: it carries sensation from the skin, teeth, gums and lining of the mouth to the brain. In the great majority of cases the neuralgia begins where the nerve enters the brainstem and a loop of a blood vessel — an ordinary artery or vein — touches or presses on it. The constant pulsation gradually damages the myelin sheath that protects the nerve, and it starts firing off pain in response to the lightest touch. This form is called classical trigeminal neuralgia.
The second possibility is secondary neuralgia, where the nerve has been damaged by another condition: a plaque of multiple sclerosis, a tumour, a cyst, a vascular malformation, or the after-effects of injury or surgery in the area. Finally, there are cases where no cause can be found; these are called idiopathic.
Classical neuralgia more often begins after the age of fifty and is somewhat commoner in women. That matters not in itself but as a pointer: the younger the person, the harder an underlying cause should be looked for.
Features that may point to another illness
The typical picture is short shocks with complete wellbeing in between. Anything that departs from it calls not for adjusting tablets but for finding the cause. Tell your doctor, and press for imaging, if any one of these is present:
- pain that is constant rather than in attacks — aching, burning, not letting up for hours;
- numbness or reduced sensation in the face — part of the cheek, lip or chin feels foreign;
- weakness of the chewing muscles: the jaw deviates to one side, it is hard to clench the teeth, chewing has gone slack;
- pain on both sides of the face;
- onset of the illness at a young age;
- hearing loss, double vision, dizziness, unsteadiness or visual change on the painful side;
- pain that responds to none of the medicines prescribed, or a picture that is changing quickly.
Multiple sclerosis or a tumour at the cerebellopontine angle can lie behind such features, and an MRI scan of the brain is needed in these cases — the investigation that shows a compressing vessel, a plaque of demyelination or a space-occupying lesion alike. Having one of these features does not mean there is a tumour; it means the diagnosis cannot rest on the description of the pain alone.
Why ordinary painkillers do not work
This is one of the most important practical differences between trigeminal neuralgia and other facial pain. Paracetamol, ibuprofen and the usual painkillers are all but useless here, and raising the dose changes nothing except the load on the stomach and kidneys. The reason lies in the nature of the pain: it is not inflammatory but neuropathic, generated by the damaged nerve itself, so what needs damping down is abnormal electrical activity rather than inflammation.
What does work are anticonvulsants — the same classes of drug used in epilepsy. They slow the conduction of abnormal impulses along the nerve and in most people markedly reduce the attacks or stop them altogether. Carbamazepine is usually the first choice; if it is not tolerated or the effect is insufficient, the doctor moves on to oxcarbazepine, lamotrigine, gabapentin, pregabalin or baclofen, sometimes in combination.
A doctor directs the process, and these medicines are neither started nor stopped on your own initiative. The dose is built up slowly over weeks to avoid drowsiness, dizziness, unsteadiness and confusion; they are taken continuously rather than only when the pain strikes; and if remission comes, the dose is tapered down just as gradually. Stopping abruptly or increasing too fast is dangerous. During treatment the doctor checks blood counts and liver tests from time to time, and if you are pregnant or planning a pregnancy the regimen is reviewed in advance, since some of these drugs are not suitable then.
When medicines stop helping
Over the years the effect of anticonvulsants can fade and the side effects can become intolerable. This is not a dead end: surgical options exist, and it is worth learning about them in advance rather than when you have nothing left. The neurologist makes the referral and the decision is taken together with a neurosurgeon.
There are two fundamentally different strategies. The first is to remove the cause: microvascular decompression, an operation in which the surgeon works through a small opening in the skull to lift the vessel away from the nerve and place a soft cushion between them. It is the largest of the procedures used, is done under general anaesthetic and carries risks, but it gives the most durable relief and leaves the nerve undamaged.
The second strategy is to dull the conduction of pain along the nerve. This covers the percutaneous procedures performed through the cheek, in which a needle is guided to the nerve ganglion and acts on it with heat, glycerol or an inflated balloon, and also stereotactic radiosurgery, a targeted beam of radiation to the nerve root with no incision at all. These are easier to tolerate and suit older people and anyone for whom major surgery is out of the question, but their effect is more often limited in time, and their characteristic consequence is lasting numbness over part of the face. The choice is always a trade-off and belongs in a conversation with your doctor, weighing your age, other conditions, how long the illness has run and what matters more to you — durability or a gentler procedure.
Life between attacks, and when help is needed at once
This illness is not confined to the minutes of pain. People lose weight because they are afraid to chew, stop washing their face and shaving, cancel meetings and conversations, and live in constant expectation of the next jolt. In time that turns into insomnia, anxiety and depression — all of which can be treated, and all of which should be reported to the doctor just as the pain is, rather than endured as an inevitable extra.
What helps day to day: keep eating and drinking enough even on bad days, switch to soft or warm food if you need to, shield your face from the wind with a scarf, avoid washing in cold water, and keep a brief diary of attacks and triggers — it is genuinely useful to the doctor when tuning treatment.
Pain of this severity can drive people to despair, and that has to be said openly. If thoughts of harming yourself or of suicide appear, help must be sought immediately — from your own doctor the same day, from an urgent mental health service, or at the emergency department of the nearest hospital. If the situation is life-threatening, call an ambulance (in Spain, Italy, Portugal, Poland and Ukraine the single European number 112 is in use). Such thoughts are not weakness of character but a consequence of unrelenting pain, and they pass once the pain is brought under control. Contact a doctor immediately as well if, while taking an anticonvulsant, you develop a widespread skin rash with blisters, a high temperature or ulcers in the mouth: this is a rare but serious reaction to the medicine.
Online consultation
Trigeminal neuralgia is precisely the sort of condition where a conversation decides a great deal. The diagnosis rests above all on the description of the pain: its character, how long an attack lasts, where it is felt and what sets it off. An online consultation makes it possible to go through that picture in detail, separate the neuralgia from toothache, cluster headache, temporomandibular joint pain and post-herpetic neuralgia, weigh up whether an MRI scan is needed, and work out which specialist to see next.
Treatment already under way is also convenient to review remotely: how the medicine is being tolerated, what to do about side effects, why it should not be abandoned at the first improvement, and when it makes sense to raise the question of surgery. If the picture does not fit the typical one, or any of the features listed above have appeared, the doctor will say so plainly and arrange a face-to-face assessment.
This material is for information only and does not replace medical advice.

Consult with a doctor about Trigeminal neuralgia (tic douloureux)
Discuss your symptoms and possible next steps with a doctor online.
Online doctors for Trigeminal neuralgia (tic douloureux)
Discuss your symptoms and possible next steps for Trigeminal neuralgia (tic douloureux) with a doctor online.



